Implants · DENTALVIEW GUIDE
Questions to ask when bone grafting is discussed
Ask how the need, scope, material, timeline and cost relate to your own examination and imaging.
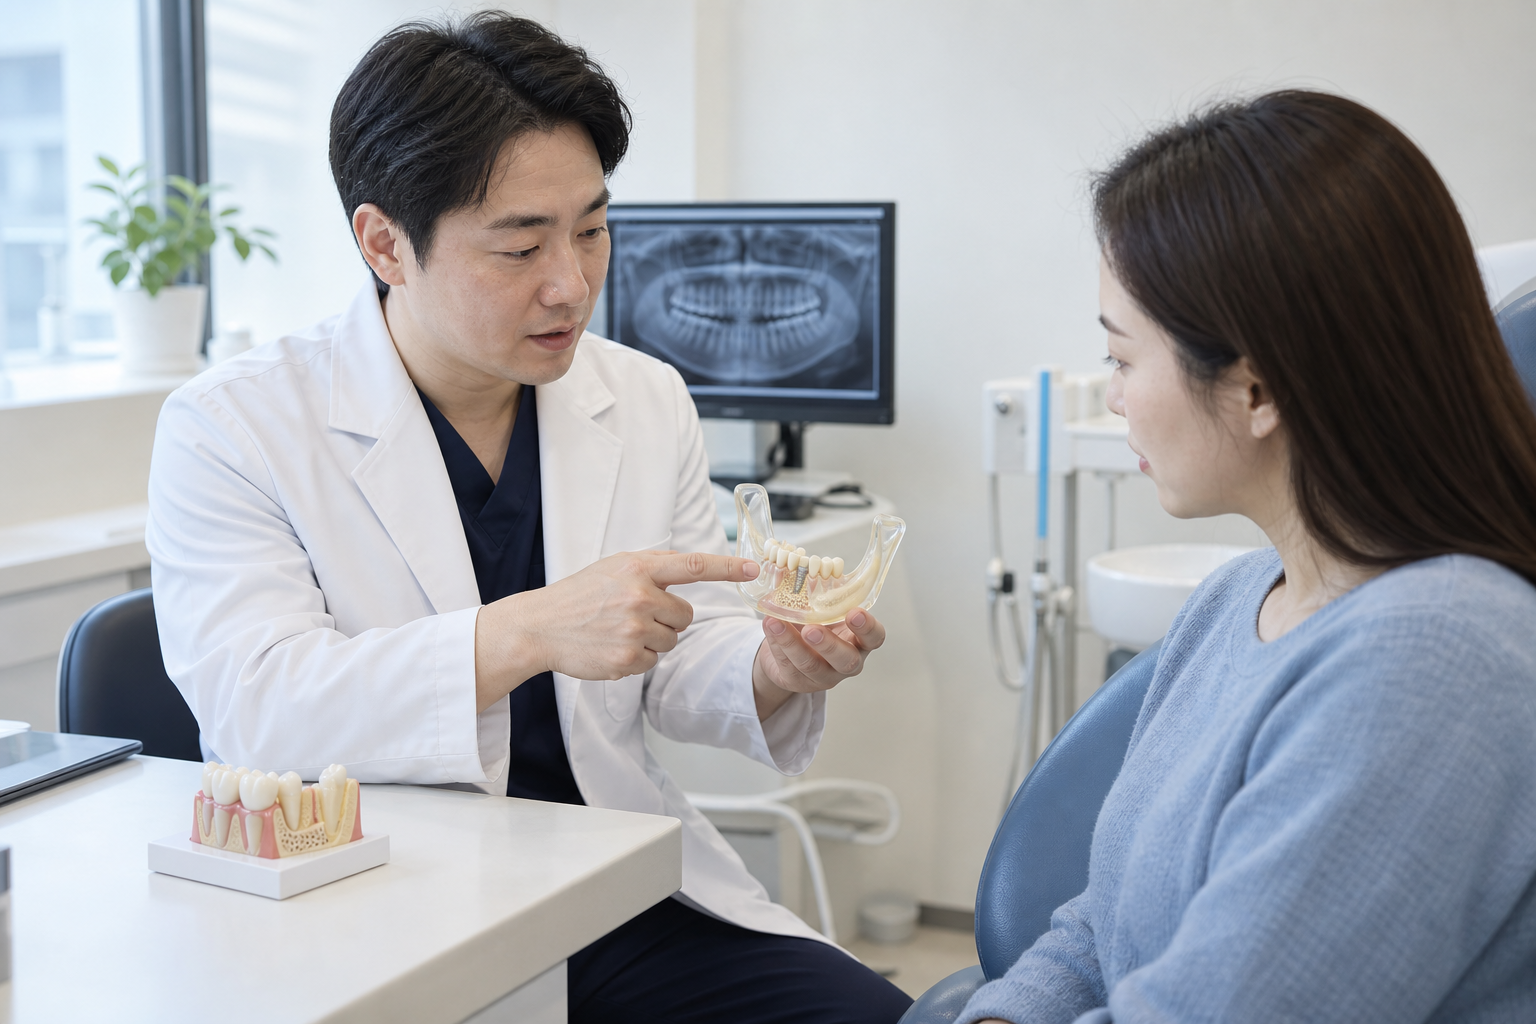
Ask how the need, scope, material, timeline and cost relate to your own examination and imaging.
A graft cannot be compared from 'you need it' alone. Identify where and how much bone is deficient and how that affects placement.
The KDCA describes examination, imaging and grafting when indicated, but individual need and extent require clinical assessment.
1. Locate the deficiency in three dimensions
The proposal changes depending on whether height, width or a specific wall is deficient.
Ask the clinician to point out the deficient area and intended implant position together. One view or measurement cannot define the whole surgical difficulty.
- Ask the clinician to point out the deficient area and intended implant position together.
- One view or measurement cannot define the whole surgical difficulty.
Official sources for this sectionKDCA National Health Information Portal: Dental implant
2. Separate the purpose of grafting
A graft may enable placement, cover exposure or support contour; each purpose has a different target.
Record the purpose, success criterion and alternative if grafting is omitted. Vague claims such as 'stronger' do not quantify the expected benefit.
- Record the purpose, success criterion and alternative if grafting is omitted.
- Vague claims such as 'stronger' do not quantify the expected benefit.
Official sources for this sectionKDCA National Health Information Portal: Dental implant
3. Ask about material and harvest site
Autogenous, allogeneic, xenogeneic and synthetic materials differ in source, mixtures and whether harvesting is needed.
Confirm material class, rationale, harvest site, alternatives and cost difference. Material category alone cannot predict individual outcomes.
- Confirm material class, rationale, harvest site, alternatives and cost difference.
- Material category alone cannot predict individual outcomes.
Official sources for this sectionKDCA National Health Information Portal: Dental implant
4. Compare simultaneous and staged approaches
Depending on bone and primary stability, grafting and placement may be combined or staged.
Compare visits, healing time, temporary tooth and conversion criteria. The timeline varies with findings and healing response.
- Compare visits, healing time, temporary tooth and conversion criteria.
- The timeline varies with findings and healing response.
Official sources for this sectionKDCA National Health Information Portal: Dental implant
5. Clarify complications and fallback plans
Infection, wound opening, material exposure or loss and sensory change may require different responses.
Obtain expected recovery, contact criteria, retreatment scope and cost policy beforehand. Risk discussion neither predicts occurrence nor guarantees an outcome.
- Obtain expected recovery, contact criteria, retreatment scope and cost policy beforehand.
- Risk discussion neither predicts occurrence nor guarantees an outcome.
Official sources for this sectionKDCA National Health Information Portal: Dental implant
A same-condition consultation table
Record the evidence, effect on your plan and unresolved condition—not only yes or no.
| Criterion | Before the visit | At consultation | Interpretation limit |
|---|---|---|---|
| Locate the deficiency in three dimensions | Ask the clinician to point out the deficient area and intended implant position together. | Which dimension is deficient, and how does it overlap the planned position? | One view or measurement cannot define the whole surgical difficulty. |
| Separate the purpose of grafting | Record the purpose, success criterion and alternative if grafting is omitted. | What specific problem is the graft meant to solve, and how will it be checked? | Vague claims such as 'stronger' do not quantify the expected benefit. |
| Ask about material and harvest site | Confirm material class, rationale, harvest site, alternatives and cost difference. | Which material is proposed, why, and is harvesting required? | Material category alone cannot predict individual outcomes. |
| Compare simultaneous and staged approaches | Compare visits, healing time, temporary tooth and conversion criteria. | What supports a simultaneous approach, and what would make it staged? | The timeline varies with findings and healing response. |
| Clarify complications and fallback plans | Obtain expected recovery, contact criteria, retreatment scope and cost policy beforehand. | Which symptoms require prompt contact, and how is retreatment handled? | Risk discussion neither predicts occurrence nor guarantees an outcome. |
| Cost by stage | Separate tests, placement, prosthesis and care | What triggers extra cost? | A headline price may not cover the full course |
| Clinician and follow-up | Record names and contact route | Who handles changes or urgent issues? | Institution size does not prove continuity |
What to verify
Ten questions to ask verbatim
- Which dimension is deficient, and how does it overlap the planned position?
- What specific problem is the graft meant to solve, and how will it be checked?
- Which material is proposed, why, and is harvesting required?
- What supports a simultaneous approach, and what would make it staged?
- Which symptoms require prompt contact, and how is retreatment handled?
- What is confirmed now, and what waits for further tests?
- What realistic alternatives include tooth preservation, a bridge or a denture?
- Can I receive stage costs and added-cost triggers in writing?
- Who actually handles each stage, and how are handoffs managed?
- How do I distinguish expected recovery from reasons to call promptly?
FAQ
FAQ
What matters most when checking locate the deficiency in three dimensions?
The proposal changes depending on whether height, width or a specific wall is deficient. Ask the clinician to point out the deficient area and intended implant position together. One view or measurement cannot define the whole surgical difficulty. At consultation, ask “Which dimension is deficient, and how does it overlap the planned position?” and record both the supporting finding and anything still unresolved.
What matters most when checking separate the purpose of grafting?
A graft may enable placement, cover exposure or support contour; each purpose has a different target. Record the purpose, success criterion and alternative if grafting is omitted. Vague claims such as 'stronger' do not quantify the expected benefit. At consultation, ask “What specific problem is the graft meant to solve, and how will it be checked?” and record both the supporting finding and anything still unresolved.
What matters most when checking ask about material and harvest site?
Autogenous, allogeneic, xenogeneic and synthetic materials differ in source, mixtures and whether harvesting is needed. Confirm material class, rationale, harvest site, alternatives and cost difference. Material category alone cannot predict individual outcomes. At consultation, ask “Which material is proposed, why, and is harvesting required?” and record both the supporting finding and anything still unresolved.
What matters most when checking compare simultaneous and staged approaches?
Depending on bone and primary stability, grafting and placement may be combined or staged. Compare visits, healing time, temporary tooth and conversion criteria. The timeline varies with findings and healing response. At consultation, ask “What supports a simultaneous approach, and what would make it staged?” and record both the supporting finding and anything still unresolved.
What matters most when checking clarify complications and fallback plans?
Infection, wound opening, material exposure or loss and sensory change may require different responses. Obtain expected recovery, contact criteria, retreatment scope and cost policy beforehand. Risk discussion neither predicts occurrence nor guarantees an outcome. At consultation, ask “Which symptoms require prompt contact, and how is retreatment handled?” and record both the supporting finding and anything still unresolved.
Can online information settle this decision?
A graft cannot be compared from 'you need it' alone. Identify where and how much bone is deficient and how that affects placement. Online information is a starting point for questions, not a substitute for examination and the treating clinician's explanation. Use these items as a checklist and mark missing information as unverified, not absent.
If two clinics disagree, what should I align first?
The KDCA describes examination, imaging and grafting when indicated, but individual need and extent require clinical assessment. First confirm that both clinics used the same records, goals and cost scope, then document why their answers differ and which further tests each needs. Align the actual clinician and follow-up scope as well as price and time.
When should I pause and seek more information?
A graft may enable placement, cover exposure or support contour; each purpose has a different target. Pause when the supporting findings, actual clinician, total scope or problem-response plan remains unclear. Ask for the missing record before committing; only an examining clinician can judge urgency. Record when the review will be completed and the next action so necessary care is not lost during the pause.